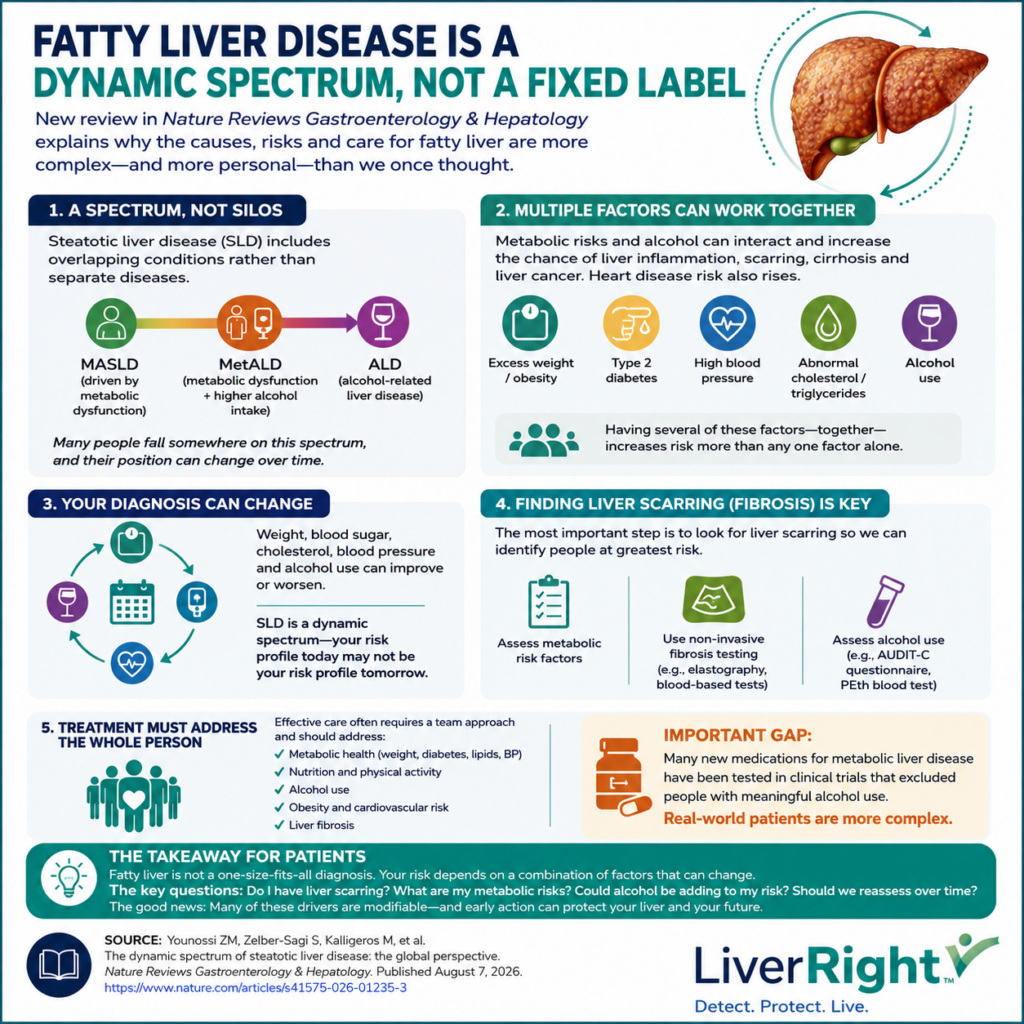
Published August 7, 2026 in Nature Reviews Gastroenterology & Hepatology, “The dynamic spectrum of steatotic liver disease: the global perspective“ makes an important point for patients: fatty liver disease is not always caused by just one thing. Metabolic health and alcohol can overlap, and a person’s risk can change over time.
Fatty Liver Disease Is More of a Spectrum Than a Label
For years, fatty liver disease was often divided into fairly simple categories — metabolic versus alcohol-related. The authors argue that real life is much more complicated.
Today, the broader term steatotic liver disease (SLD) includes conditions such as MASLD (metabolic dysfunction-associated steatotic liver disease), MetALD (metabolic dysfunction plus higher alcohol intake), and alcohol-related liver disease. Rather than being completely separate diseases, these conditions frequently overlap.
Why this matters for patients
Many people with fatty liver have more than one risk factor. These can include excess weight or obesity, type 2 diabetes, high blood pressure, abnormal cholesterol or triglycerides, and alcohol use. Having several of these factors together can increase the likelihood that liver fat progresses to inflammation, fibrosis (scarring), cirrhosis and serious liver complications. Cardiovascular disease is also an important concern.
One of the review’s most important messages is that metabolic risk and alcohol can work together to damage the liver. Someone with diabetes, obesity or other metabolic problems may therefore be more vulnerable to the effects of alcohol than a simple diagnostic label suggests.
Your diagnosis can change over time
Weight, blood sugar, cholesterol and blood pressure can improve or worsen. Alcohol consumption can also change.
That means someone classified as having MASLD today could fall into a different category later. The authors argue that clinicians should think of steatotic liver disease as a dynamic spectrum rather than assigning a label once and assuming it will always remain accurate.
Finding liver scarring may be more important than the label
For patients, an especially practical takeaway is that identifying fibrosis — liver scarring — is critical.
The review recommends combining assessment of metabolic risk factors and alcohol use with non-invasive fibrosis testing to identify people at greatest risk of progressive liver disease. Alcohol assessment can include questionnaires such as AUDIT-C and, in appropriate circumstances, blood biomarkers such as phosphatidylethanol (PEth).
Treatment needs to address the whole person
Managing fatty liver disease isn’t simply about “losing weight” or “stopping alcohol.” Depending on the individual, care may need to address several issues simultaneously: metabolic health, nutrition and physical activity, alcohol consumption, obesity, diabetes, cardiovascular risk and liver fibrosis. The authors therefore emphasize coordination among primary care, liver specialists, endocrinology, cardiology, nutrition and addiction medicine when appropriate.
There is also an important gap in current drug research. Many newer medications being studied or used for metabolic liver disease have been evaluated in trials that exclude people with meaningful alcohol consumption. That means clinical trial populations don’t always resemble the patients clinicians see every day.
The patient takeaway
Fatty liver disease shouldn’t be viewed as a fixed diagnosis with a single cause. Metabolic health, alcohol exposure and liver scarring can all change over time.
If you have fatty liver, the important questions aren’t only “What type do I have?” but also “Do I have liver scarring? What metabolic risk factors do I have? Could alcohol be adding to my risk? And should these risks be reassessed over time?”
The encouraging part is that several of these drivers are potentially modifiable. Identifying them early — before substantial liver scarring develops — creates an opportunity to reduce future risk.